
Bringing FIRST to life
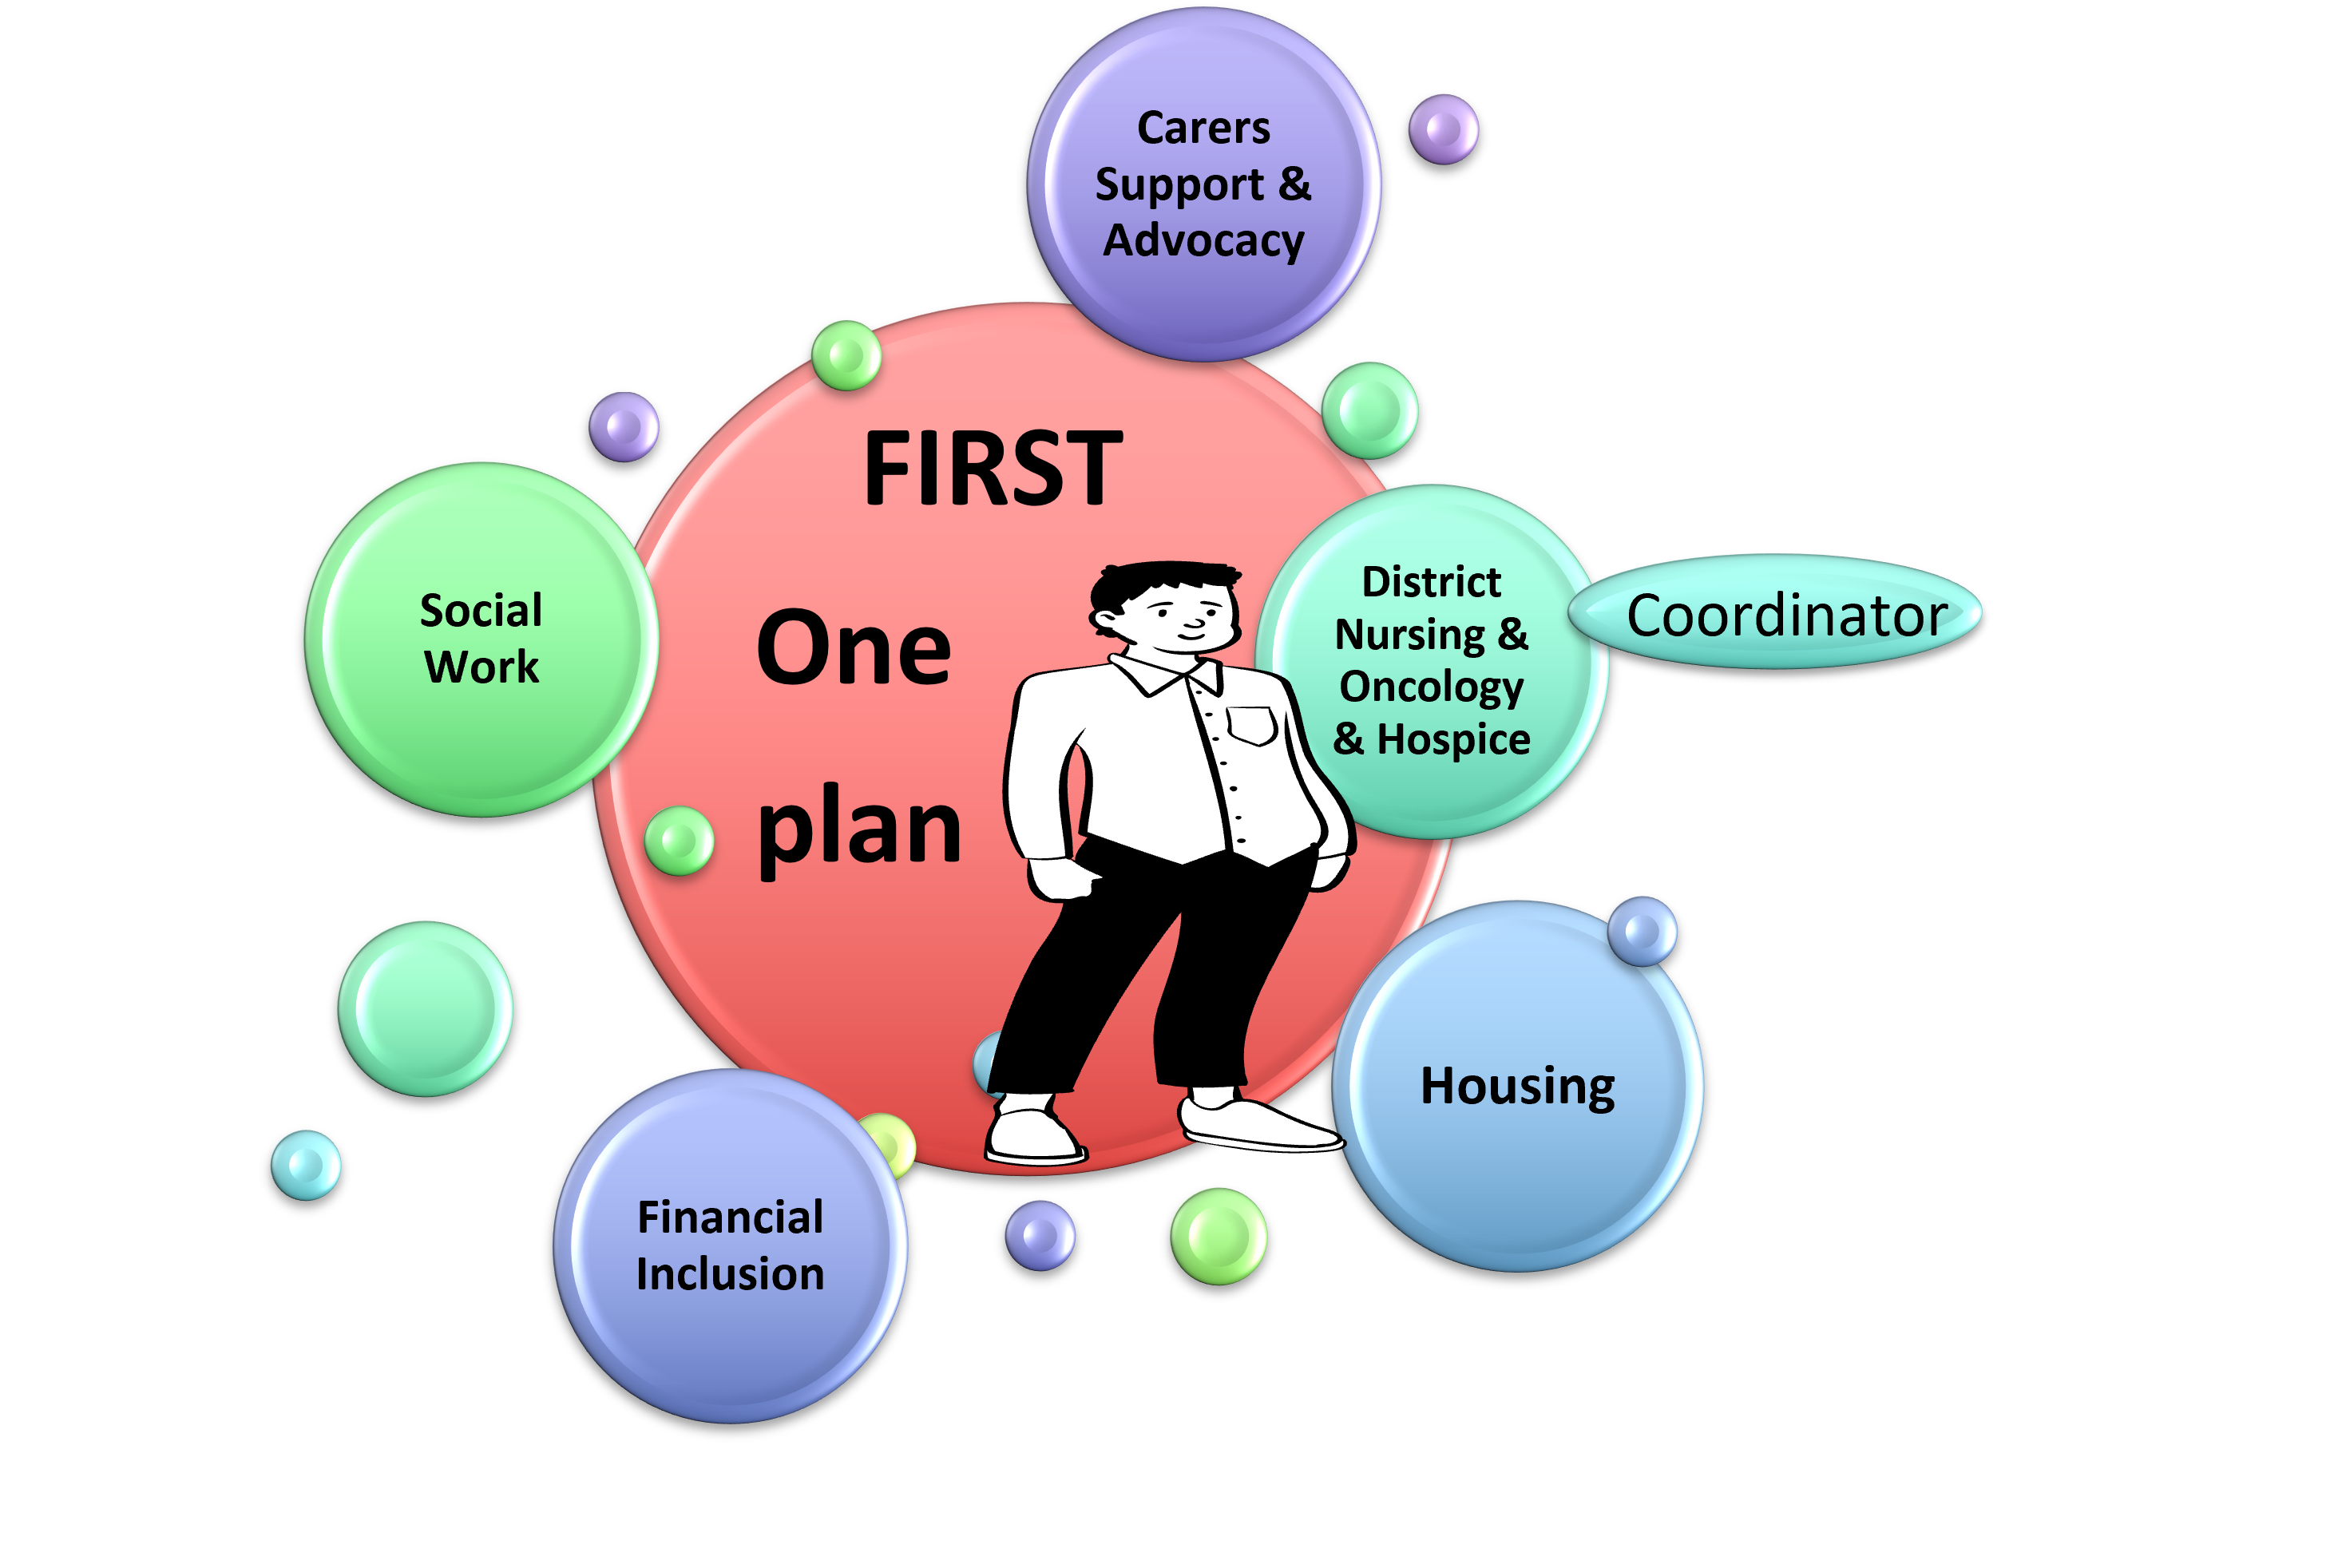
We'd like to share an anonymised example that demonstrates how GIRFE principles can translate into practical action.
Mr A was a 52-year-old man who had recently been released from prison. Shortly after his release, he received a diagnosis of terminal cancer and had started palliative chemotherapy. He was experiencing significant pain, had no settled accommodation, very limited income and was living in a shed behind a friend's property. The accommodation consisted of little more than a bed and a kettle. A district nurse on first visit to the property became concerned about both his health and living circumstances and made contact through FIRST.
If we think about this situation through a traditional service lens, there were multiple issues:
- housing
- health
- financial
- social work
- carer support
- potential advocacy
What struck us was that none of those individual descriptions really reflected what mattered to the person.
When the nurse spoke with Mr A, his priorities were actually very clear. He wasn't asking for lots of services. He told us: "I want to be pain free and stay independent for as long as possible". That statement became the focus for our planning.
Rather than starting with organisational responsibilities, FIRST enabled us to start with the person, their wishes and their outcomes. The referral immediately highlighted complexity, vulnerability and the need for coordinated working across multiple agencies.
Importantly, we were able to bring those perspectives together early rather than waiting for separate assessments and referrals to occur at different times. For us, this case illustrates something important about GIRFE:
- people rarely present with needs that fit neatly within a single professional boundary
- their circumstances, strengths, aspirations and challenges are interconnected
- what they need from us is not multiple separate responses, but one coordinated response built around what matters most to them
How FIRST enabled a coordinated response
Once the referral came into FIRST, the focus became bringing together the right people to understand the whole situation and agree a coordinated response. The district nurse's concerns extended well beyond health needs. There were significant housing issues, financial concerns, social isolation, uncertainty about future care arrangements and increasing pressure on the friend who was providing support.
Because these issues were discussed through FIRST, we were able to consider them together rather than separately. An urgent joint assessment was arranged involving social work and district nursing. Through the discussion, it became clear that several services had an important contribution to make:
- housing colleagues began working to identify more suitable accommodation options
- financial Inclusion services were engaged to maximise income and ensure Mr A was receiving all benefits and entitlements available to him
- advocacy support was offered so that he could participate fully in discussions and decisions about his future
- support was arranged for the friend who had effectively become an unpaid carer, helping to reduce the risk of carer breakdown
- district nursing and specialist palliative care services continued to support symptom management, pain control and treatment planning
Most importantly, these interventions were not planned in isolation. Everyone understood:
- what mattered to Mr A
- what role they were playing
- what outcomes we were collectively trying to achieve
- how their contribution linked to the wider plan
This is where FIRST adds most value. No individual service needed to solve every problem. Instead, services worked together to create a coordinated response built around the person's priorities.
The conversation was not: Which service owns this case?
The conversation became: What needs to happen for this person to remain pain free, maintain independence and live with dignity for as long as possible?
That shared understanding allowed support to be mobilised quickly and appropriately.
For us, this is a practical example of GIRFE in action. It demonstrates how integrated working can move beyond coordination between organisations and become coordination around a person's life, circumstances and goals
The outcomes for Mr A
When we first became involved after a referral from Mr A’s friend, Mr A was living in highly unsuitable accommodation, experiencing significant pain, facing financial hardship and trying to cope with a new terminal diagnosis. His friend was providing support but had little formal assistance themselves.
Following the coordinated actions agreed through FIRST the very next day, important changes began to happen:
- accommodation issues were addressed and temporary housing arrangements were offered though not initially accepted due to distance from his friend. Currently longer-term solutions are being explored
- Financial Inclusion colleagues worked with Mr A to maximise his income and access available benefits, reducing some of the financial pressures he was experiencing
- health colleagues coordinated his pain management and palliative care support, helping ensure his treatment and symptom management reflected his wishes and priorities
- advocacy support helped him remain involved in decisions about his care and future planning
- the friend who was supporting him was recognised as an unpaid carer and offered appropriate support, helping sustain that important relationship
What is important is that these outcomes did not happen because one service took ownership of everything. They happened because services worked together around a shared understanding of what mattered most to the person. For Mr A, success wasn't measured by how many services became involved. Success was measured by whether he could:
- remain as independent as possible
- have better control of his pain and symptoms
- maintain dignity and choice and stay connected to the people important to him
- he could feel supported rather than overwhelmed by services
This is where GIRFE and FIRST come together. The focus moves away from organisational activity and towards personal outcomes.
The outcome was not simply a series of referrals. The outcome was one coordinated plan built around the person's wishes, strengths and circumstances. Even when we wondered how a community electric bed and commode would fit in a shed.
For us, this case demonstrates what can happen when organisations see the whole person rather than just the part of the situation that falls within their own service boundaries. And it reinforces one of our most important learning points – people rarely need a single service solution; they need a coordinated response built around the life they are trying to live.
